
Chairside 46
A Clinical Case Review: Possible Causes of Failure of the Implant in Region 5, Upper Left
After two prostheses were made on the implant in region 5, upper left, a patient developed pain and inflammation of the gingiva around it, and the implant screw also loosened on both occasions. I did not treat or examine this patient; this analysis is based only on the history, PA radiographs and CBCT. Below, we review the possible causes of this failure and the points that should be checked at direct examination.
History and course of treatment (according to the patient’s report)
- 1404/4/31: Implant surgery in the region of tooth 5, upper left.
- 1404/9/2: Delivery of the first prosthesis.
- About two months after delivery of the prosthesis, pain began only in the gingiva of the same tooth. The prosthesis was not mobile.
- 1405/2/8: First visit. The treating dentist took a radiograph and said he would remove the prosthesis at his own expense. Because the cement was permanent, according to the patient he broke the prosthesis and took it out. After a new impression, the second prosthesis was delivered on 1405/2/23.
- During the period when the patient had no prosthesis, the gingival pain had completely resolved.
- About one month after the second prosthesis, the gingival pain started again.
- 1405/4/28: Visit to another clinic. A radiograph was taken, and the patient was told that apparently there was no problem and that follow-up should be with the treating dentist.
- 1405/8/2: Most recent visit. The second prosthesis was also broken and the implant screw was removed. The dentist said that the screw inside the implant had become loose and that the same problem had existed at the first visit, when a new screw was placed. The dentist said that although the implant is an original Korean one, it can sometimes have a problem, and a problem in the implant or the bone was raised, and a CBCT was prescribed. Because of gingival infection, amoxicillin was prescribed.
Radiographs
Clinical analysis
The time interval between delivery of the prosthesis and reaching this amount of bone loss is short. This course is not the result of a single factor, and several biomechanical and biological factors can be identified in it.
1. Incomplete abutment seating in the first prosthesis
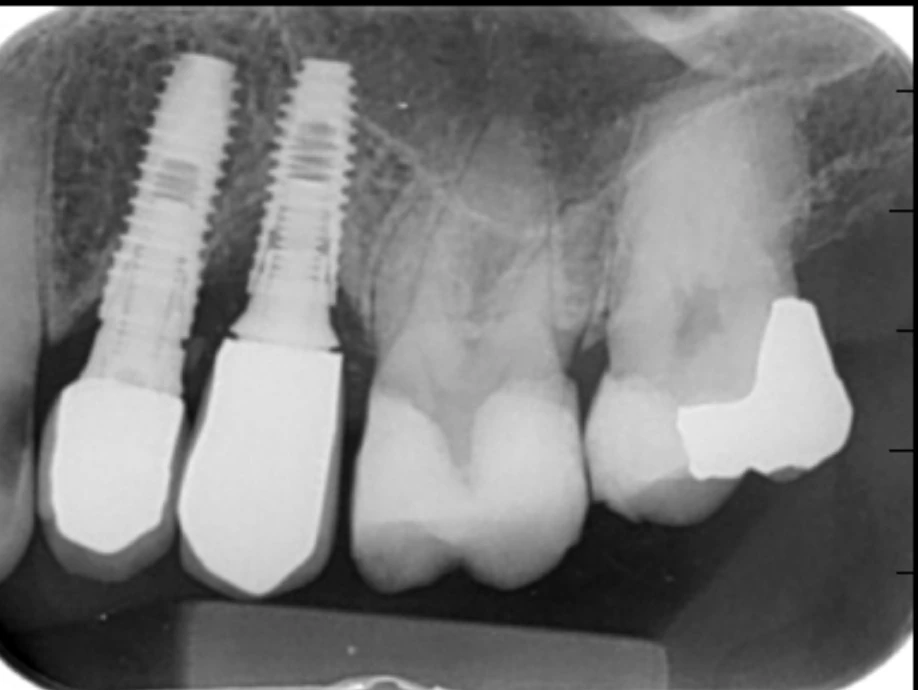
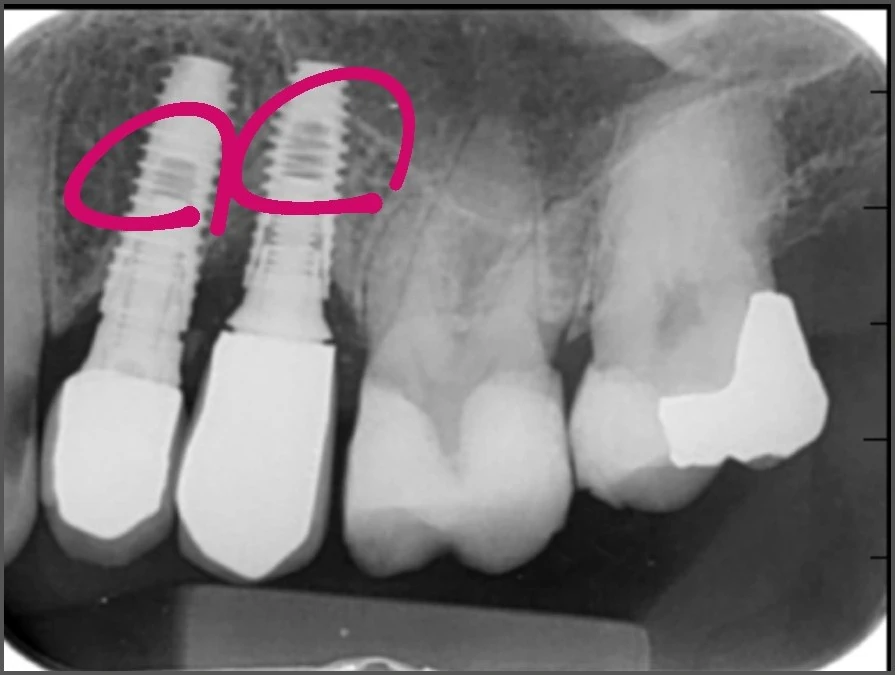
In the radiograph of the first visit (Figure 2), the space at the screw end of implant 5 is larger than that of the adjacent implant (4). This appearance indicates either that the screw is loose or that the abutment was not fully seated on the fixture platform and the screw was tightened in that position. Because the patient’s complaint from the beginning was gingival inflammation and pain and not mobility of the prosthesis, the second possibility is more likely: a loose screw usually shows itself through movement of the crown, whereas an abutment that is not fully seated can remain immobile and at the same time create a permanent gap at the fixture-abutment interface, which is a site of bacterial accumulation and chronic inflammation.
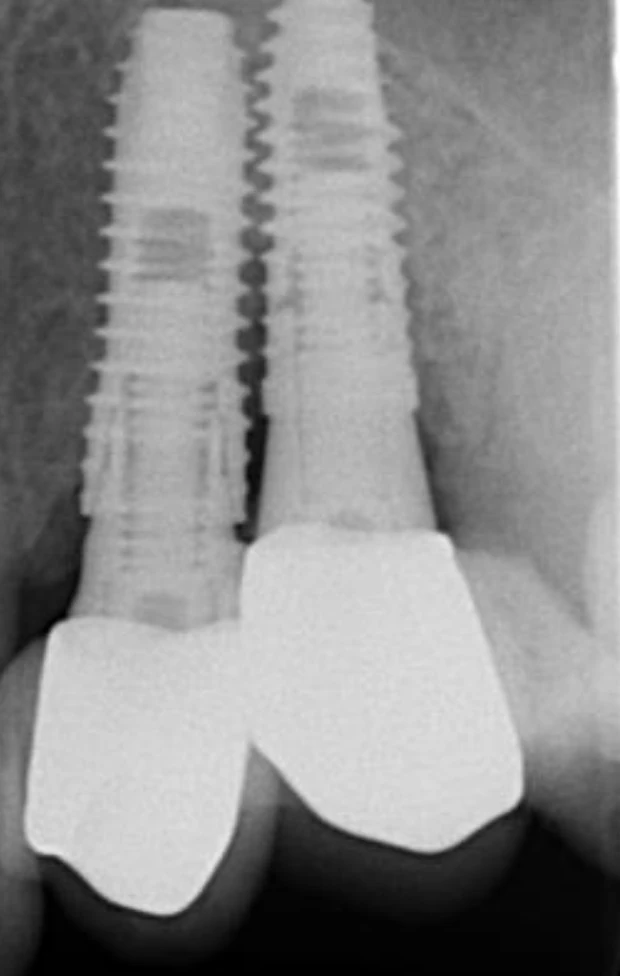
Comparison with the second radiograph (Figure 3) supports this impression. In the second radiograph, the space at the screw end is equal in implants 4 and 5, which means that after the screw was replaced and the second prosthesis was made, the abutment was fully seated. So the seating problem seen in the first radiograph had been resolved in the second prosthesis.
The important point is that at both visits the patient presented because of gingival inflammation and pain. At the first visit, incomplete abutment seating was one of the factors of inflammation, but at the second visit the inflammation returned even though the abutment was fully seated. Therefore the recurrence of symptoms with the second prosthesis cannot be attributed to abutment seating, and its main cause should be sought in the permanent cement with a deep margin and the subgingival contour of the prosthesis, which had not changed in the second prosthesis either, and a possible crack of the fixture (sections 2 to 4). In the first prosthesis, the hex of the abutment was probably not seated properly in the implant, which should be checked at direct examination.
2. Permanent cement with a deep margin
Both prostheses were cemented with permanent cement, and their margins are deeper than usual in the PA radiographs. The combination of a deep margin with permanent cement increases the likelihood of excess cement remaining in an area that cannot be cleaned without opening a flap. Residual cement is a recognized cause of inflammation and bone loss around implants. Permanent cement also meant that on both occasions the prosthesis had to be broken to be removed, and it was not possible to examine and re-torque the abutment without destroying the prosthesis.
The complete resolution of pain in the period when the patient had no prosthesis is consistent with this picture: in that period, both the excess cement and the poorly seated abutment had been removed.
3. Subgingival contour of the prosthesis
In the PA radiographs, the contour of both prostheses in the area above the finish line, that is, the subgingival part, is bulkier than appropriate. This part of the emergence profile presses directly on the soft tissue and, together with the deep margin, reduces the cleansability of the area. The combination of residual cement, an open interface and an inappropriate contour creates a suitable environment for peri-implantitis.
4. Possible crack of the fixture
In the second radiograph, at about the level of the screw end of the abutment of implant 5, the continuity of the outer wall of the fixture is interrupted on both the mesial and distal sides and at one horizontal level. This appearance raises the possibility of a transverse crack in the fixture. This level is a common site of fixture failure, because the implant wall is thinner there. In the first radiograph, no clear discontinuity is seen at this same level. The probable course is that the incomplete seating of the abutment in the first prosthesis concentrated the load on the screw and the thin wall of the fixture at this level and set the stage for the crack. Removing the first crown by breaking it, and the impact from that, may also have created or aggravated the crack, and function under the second crown has made it progress. Accordingly, the origin of the two episodes of inflammation was probably not the same: the first inflammation was more related to the open abutment interface, and the second more related to the cement, the contour and the fixture crack. The presence of a crack becomes certain only after the components are removed and examined directly.
5. Buccal bone status
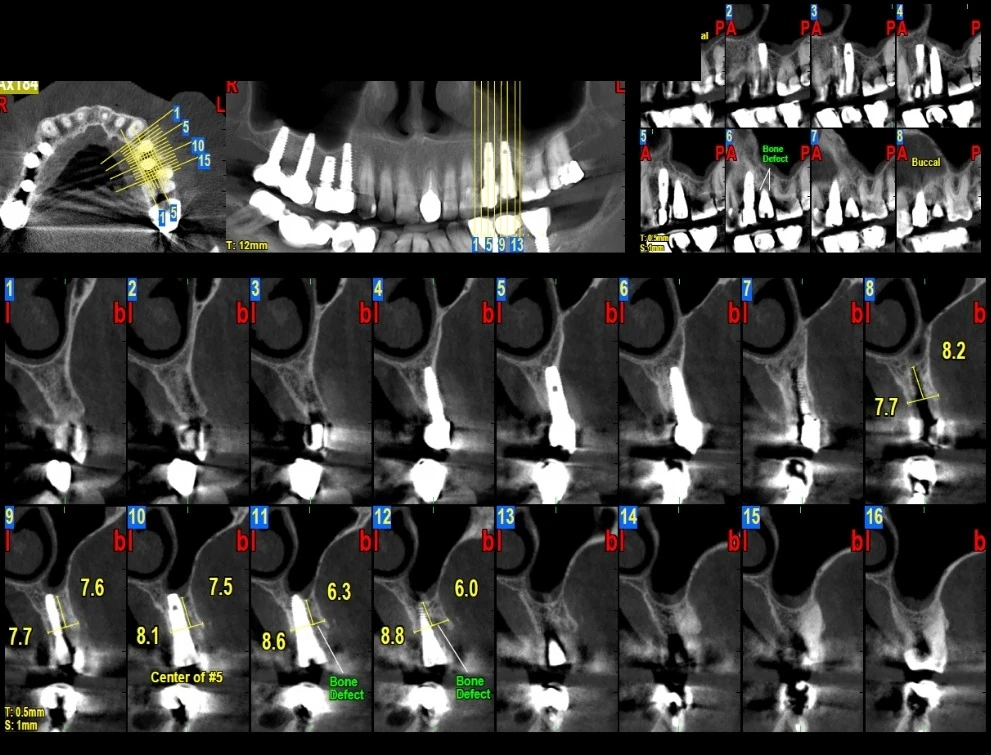
In the CBCT cross-sectional slices (slices 11 and 12), a bone defect on the buccal side of the fixture is evident. The maxillary premolar region inherently has a thin buccal plate, and it is possible that the thickness of the buccal bone was small from the beginning and had little resistance to inflammation. Because this CBCT was taken about fifteen months after surgery and a radiograph immediately after surgery is not available, it cannot be said with certainty whether the defect was present from the beginning or is the result of later inflammation. In slices 9 and 10, the fixture is located within the ridge.
6. Screw loosening
Regarding the loosening of the screw at the second visit, even though the abutment was fully seated: its cause should be found at examination, including occlusal contacts and screw torque. A slight mismatch of the components, which is seen, for example, in non-original components and cannot be seen on a radiograph, may also contribute. A possible crack of the fixture at the level of the screw end can itself also be the cause of screw loosening, by destroying the grip of the threads and the hex. These factors aggravate each other in a cycle.
Regarding the possibility of a defect in the implant itself: a manufacturing defect of the fixture is rare and can be considered only after the common causes (seating, torque, occlusion) have been excluded and the connection has been examined directly.
(An opinion outside the framework of the analysis, from a psychological point of view: several sentences in the history are meaningful to me. When, after the first inflammation, the dentist says he will replace the prosthesis at his own expense, my feeling about this combination of words is that it is a sign of anxiety. The fact that, without being asked by the patient, he mentioned that the components were original is a sign of mental preoccupation with an event that he knows about and the patient does not, and it may even indicate that the components were not original. The components not being original can itself cause a mismatch between the abutment and the fixture, incomplete seating and screw loosening. And when the patient uses the word "broke" for removing the crown, for me it is a description of impacts that he felt, and these impacts may have damaged the fixture.)
Diagnostic points
- The space at the screw end in the radiograph of the first visit, compared with implant 4, was from that stage a sign of a problem in abutment seating or the screw, and its cause needed to be determined before making the second prosthesis.
- In the radiograph of the second clinic (1405/4/28), the space at the screw end is equal in the two implants and the abutment is seated. So the inflammation at the second visit occurred with a seated abutment, and its cause should be sought in the cement, the contour of the prosthesis and the possible crack of the fixture.
- After removing the abutment, the internal connection of the fixture (hex and thread) and the wall of the fixture at the level of the screw end (for a crack) should be examined directly.
- Complete abutment seating should be confirmed with a new abutment and a radiograph perpendicular to the interface. If seating is not complete even with a new abutment, soft tissue or bone interference on the platform or damage to the connection should be considered.
- Probing depth around the fixture, presence of pus, bleeding on probing and fixture mobility should be recorded.
- The occlusion of the area should be examined for premature contacts and contacts in lateral excursion.
- The real extent of the buccal bone defect becomes clear only when a flap is opened.
Summary and treatment path
The overall picture of this case: in the first prosthesis, the abutment was not fully seated, and together with permanent cement and an inappropriate contour it caused inflammation. In the second prosthesis, abutment seating was resolved, but the permanent cement with a deep margin and the bulky subgingival contour did not change, a possible crack of the fixture, which may have been caused by stress concentration or by the impact of removing the first crown, was added, and the inflammation returned. The buccal bone has also been resorbed under this repeated inflammation.
The prognosis of this implant is currently poor, but if the fixture has no mobility or crack and the internal connection is intact, it is possible that the implant can be retained with a screw-retained prosthesis with a correct contour, without cement and with an adjusted occlusion, together with surgical treatment of peri-implantitis and cleaning of the area. The decision between this path and removing the fixture and reconstructing the site depends on the findings of direct examination and must be made by the surgeon after opening a flap and seeing the real extent of the defect. Until these points are clarified, making a new prosthesis on this fixture is not reasonable.
This page is intended for educational use by dentists and dental students.